What is Myelodysplastic Syndrome and How Is It Treated?
Myelodysplastic syndrome (MDS) is a group of conditions that disrupt the bone marrow's blood cell production process. In individuals with MDS, the bone marrow produces immature (blast) abnormal cells instead of a sufficient number of healthy blood cells. This condition leads to a decrease in the number of healthy red blood cells, white blood cells, and platelets. Consequently, transporting oxygen throughout the body becomes difficult, the immune system weakens, and the risk of bleeding increases.
What is Myelodysplastic Syndrome?
MDS is an abbreviation for the English expression myelodysplastic syndrome. MDS is sometimes also referred to as myelodysplasia or myelodysplastic neoplasia. The course of the disease varies from person to person. While some MDS cases follow a mild course, acute myeloid leukemia may develop over time in some cases. Although the glioma-myelodysplastic relationship is rare, it can co-occur in certain genetic syndromes.
What Are the Symptoms of Myelodysplastic Syndrome?
Symptoms of MDS are mostly related to low cell counts in the blood. Some patients may not have symptoms initially, and MDS may be detected incidentally during routine blood work. Myelodysplastic anemia is one of the most common symptoms of this syndrome and can cause severe fatigue. In myelodysplastic syndrome, symptoms can manifest as fatigue, susceptibility to infections, and a tendency to bleed. Patients are usually suspected when findings such as anemia, neutropenia, or thrombocytopenia appear in blood tests. MDS may initially follow a mild course; many patients may attribute fatigue or frequent infection complaints to their age or other reasons. Therefore, MDS is sometimes detected through routine blood tests revealing anemia or other cell count abnormalities. The main symptoms are:
Fatigue and weakness: When the number of red blood cells decreases, the amount of oxygen reaching body tissues drops. This condition can lead to complaints such as fatigue, weakness, shortness of breath, or palpitations.
Susceptibility to infection: When the white blood cell count (especially neutrophils) is low, the immune system weakens, and frequent or severe infections can develop.
Easy bleeding and bruising: A decrease in the platelet (thrombocyte) count impairs clotting ability. Gum bleeding, nosebleeds, bruises on the skin, or petechiae (small red spots) may be observed.
Other symptoms: Some patients may also experience more general symptoms such as fever, bone pain, loss of appetite, or weight loss. At the same time, myelodysplastic syndrome may present with pancytopenia, meaning red blood cells, white blood cells, and platelets decrease together; however, since these symptoms can also be seen in other diseases, a doctor must be consulted for persistent complaints.
What Are the Causes of Myelodysplastic Syndrome?
Although the exact cause of MDS is generally unknown, certain risk factors have been identified. While no cause can be found in the majority of patients, the following conditions may increase susceptibility to the disease:
Advanced age and male gender: The risk of MDS increases with age; most patients are over 60 years old. It is slightly more common in males.
Inherited genetic disorders: Rare genetic syndromes such as Fanconi anemia, dyskeratosis congenita, or Diamond-Blackfan anemia can increase the risk of developing MDS.
Previous cancer treatment: Individuals who have received chemotherapy or radiotherapy in the past may develop therapy-related (secondary) MDS. In these cases, MDS usually appears 5–7 years after treatment.
Exposure to toxic substances: Long-term exposure to chemicals such as benzene and pesticides, heavy metals (mercury, lead), or factors like radiation can increase the risk of MDS.
Other factors: Smoking also slightly increases the risk.
Multiple factors may play a role in most MDS cases; nevertheless, a clear cause cannot be found in many cases. The exact pathogenesis of MDS is unknown; research shows that genetic damage in stem cells, chromosomal abnormalities, and gene mutations regulating cell division play a role in the formation of this disease.
How is Myelodysplastic Syndrome Diagnosed?
MDS is diagnosed through blood tests and bone marrow examination. While performing a blood count, parameters such as vitamin B12 and folate can also be examined; thus, other causes of anemia are ruled out. In myelodysplastic syndrome, the serum erythropoietin level is an important biochemical indicator in evaluating diagnosis and treatment response. The most important test to confirm the diagnosis of MDS is bone marrow examination. Doctors generally apply the following tests:
Complete blood count (CBC): The numbers of red and white blood cells as well as platelets are measured in the collected blood sample. In MDS, the counts of these cells are usually low (anemia, neutropenia, thrombocytopenia). Myelodysplastic syndrome should be monitored by a hematologist, and regular blood counts should be performed.
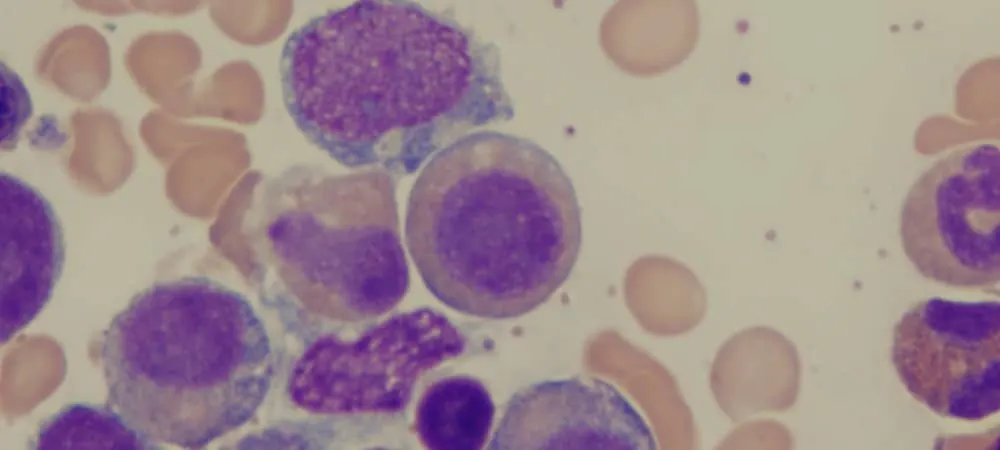
Peripheral blood smear: Blood cells are examined under a microscope, and morphological or maturation abnormalities are investigated. Findings such as an increase in immature blast cells may indicate MDS.
Bone marrow biopsy: A bone marrow sample is taken from the hip bone using a thin needle. The harvested tissue is examined in the laboratory to evaluate cell types, blast percentage, and chromosomal abnormalities. In MDS, the proportion of immature cells in the bone marrow is increased.
Cytogenetic analysis: The chromosomal structure of bone marrow cells is analyzed. The presence of specific genetic mutations or chromosomal deletions (e.g., 5q deletion) can support the diagnosis of MDS.
Based on the results of these tests, doctors determine the presence and subtype of the disease. During the diagnostic phase, other blood disorders (aplastic anemia, leukemia, etc.) are ruled out.
What Are the Treatment Methods for Myelodysplastic Syndrome?
MDS treatment is determined based on the type, severity (risk level) of the disease, and the patient's general condition. The main treatment methods are:
Close monitoring (watchful waiting): Doctors may choose to monitor the disease in low-risk patients with few symptoms. Blood tests are repeated at certain intervals; treatment is initiated if symptoms or blood values worsen. Thus, unnecessary aggressive treatments are avoided.
Supportive care: Red blood cell transfusions are given if anemia is present, and platelet transfusions if thrombocytopenia is present. If necessary, blood cell production is supported with growth factors such as erythropoietin (EPO) or G-CSF. Antibiotics or antiviral medications can be used against the risk of infection. Additionally, preventive measures such as vaccinations (flu, pneumonia vaccines) may be recommended.
Preventing iron overload: Repeated blood transfusions can lead to excess iron in the blood, which causes damage to organs such as the heart and liver. In this case, iron chelation medications can be used to remove excess iron from the body.
Immunosuppressive therapy: Particularly in the hypoplastic MDS subtype where cell production is suppressed, immune system-suppressing drugs such as antithymocyte globulin (ATG) and cyclosporine can be administered. This approach aims to increase the blood cell count.
Disease-modifying drugs: Medications that slow down the disease and increase blood cell production are administered. For instance, hypomethylation inhibitors such as azacitidine and decitabine, and lenalidomide in cases with the del(5q) chromosomal anomaly, can be used. These drugs can reduce the risk of MDS progressing to AML.
Chemotherapy: In high-risk cases or when MDS transforms into acute leukemia, chemotherapy protocols used in acute myeloid leukemia can be administered. This is generally considered for relatively young patients with a good general condition.
Stem cell transplantation: Allogeneic stem cell transplantation may be considered as the only curative chance of treatment in young patients with a good general condition. In this method, the patient's bone marrow is first cleared with high-dose chemotherapy or radiation, and then healthy stem cells obtained from a suitable donor are given to the patient. The donor cells engraft in the patient's bone marrow and begin producing normal blood cells over time.
Autophagy may play a role in regulating intracellular damage in bone marrow disorders such as myelodysplastic syndrome. Each treatment option has its own advantages and risks; doctors determine the most appropriate plan together based on the patient's general condition.
What Is the Role of Bone Marrow Transplantation in Myelodysplastic Syndrome?
Stem cell (bone marrow) transplantation is the most aggressive yet only curative method in MDS treatment. In allogeneic (donor-derived) transplantation, the patient is first cleared of existing blood cells through chemotherapy or radiotherapy. Subsequently, healthy stem cells obtained from a suitable donor are infused into the patient. Donor cells engraft in the patient's bone marrow and begin producing new, healthy blood cells. This method carries a high risk and is not applied to every patient. Post-transplantation, the patient's immune system may react against donor cells (graft-versus-host disease), or the risk of severe infection may increase. The success rate of transplantation depends on age, general health, and the degree of the disease. Additionally, the graft-versus-tumor effect, where donor cells destroy cancer cells, can contribute to the success of the treatment. Therefore, the decision for transplantation is made very carefully, evaluated jointly by the patient and the doctor.
Frequently Asked Questions
MDS usually appears at an advanced age; most patients are over 60 years old. It is slightly more common in males. Since the average age at diagnosis is around 70, it is very rare at a young age. However, individuals who have received chemotherapy or radiotherapy in the past are at risk of developing therapy-related MDS. Although rare, MDS can be seen in young people with certain inherited genetic disorders (e.g., Fanconi anemia). MDS is generally classified under blood and bone marrow cancers, but the potential of MDS to transform into leukemia is limited, and the choice of treatment is decided according to cancer treatment rules. Treatment varies depending on the patient's blood cell counts and general condition. Supportive therapies (blood transfusions, growth factors, antibiotics), drugs that slow down the disease (azacitidine, decitabine, lenalidomide, etc.), chemotherapy, and, where appropriate, stem cell transplantation therapy are applied. In low-risk cases, supportive therapies to alleviate symptoms are preferred first, while more aggressive treatments are transitioned to in high-risk cases. Applied treatments may have side effects. For example, chemotherapy can cause side effects such as nausea, vomiting, hair loss, and an increased risk of infection. Iron can accumulate in the blood as a result of erythrocyte transfusions. In stem cell transplantation, immune system issues (graft-versus-host disease), organ toxicity, and infection risk are important. Chelation therapies may be necessary to prevent iron overload, and prophylactic medications to prevent infections. Your doctor will share the benefits and risks of each treatment method with you in detail. There is currently no completely curative treatment for MDS. Existing treatments aim to slow the progression of the disease, alleviate symptoms, and preserve the quality of life. With appropriate treatment and close monitoring, many MDS patients can lead a longer and higher-quality life. Allogeneic transplantation can provide a complete cure for some patients, but for most patients, MDS is a chronic process and remains under regular monitoring. Therefore, MDS patients should be regularly monitored by a hematology-oncology specialist, and treatment plans should be carefully made by specialists.
Myelodysplastic syndrome is a disease that can be controlled with regular monitoring and the right treatment plan. Early diagnosis is of great importance in terms of quality of life and treatment success. If you or your loved ones experience symptoms such as unexplained anemia, frequent infections, or easy bruising, it is recommended that you consult an expert hematology doctor without delay.
You can contact us immediately to consult with Hisar Hospital Hematology Specialists and get detailed information.
Start with the right assessment for What is Myelodysplastic Syndrome (MDS)? Symptoms, Causes, and Treatment Methods
Share your symptoms with our specialist physicians; let us determine the right diagnosis and treatment plan together.
Warning
If your symptoms started suddenly, are progressing rapidly, or significantly restrict your daily life, consult a physician without delay.
Plan your What is Myelodysplastic Syndrome (MDS)? Symptoms, Causes, and Treatment Methods journey with our specialists.
Fill in the form or book an appointment to learn about treatment options, the process and preparation.